
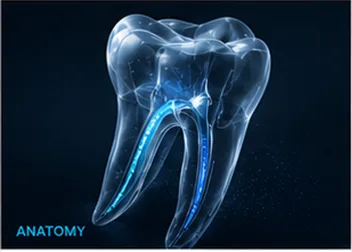
Anatomy
Reading Anatomy, Not Guessing
Clinical decisions informed by the anatomy seen in images and at the chair.
The clinical question
What does the anatomy ask you to confirm before the first shaping file enters the canal?
Radiographs, magnification, tactile feedback, and the chamber-floor map each reveal a different part of the case. Use them together to form a working anatomical hypothesis, then keep testing it as treatment progresses.
Before access
Read the tooth in more than one plane.
A straight-looking root can conceal buccolingual curvature, and roots that overlap in one projection may separate in another. Review the crown, root outline, canal width, abrupt canal disappearance, previous restorations, and the relationship to nearby anatomy before deciding the access direction.
Angled radiographs and CBCT, when clinically indicated, can clarify questions that a single projection cannot answer. Imaging should resolve a defined uncertainty; it does not replace inspection of the chamber floor or tactile confirmation of the pathway.
At the chamber floor
Use landmarks before assumptions.
Preserve the chamber-floor map long enough to read colour changes, developmental grooves, dentine shelves, and the relationship between known orifices. Refine access in controlled increments and inspect frequently rather than troughing towards an assumed canal position.
An orifice is the beginning of a question, not proof of the full route. Canals may divide, merge, curve sharply, or communicate through isthmuses. Confirm how the file behaves on withdrawal and reinsertion before committing to mechanical enlargement.
- Reconcile the clinical crown with the root axis.
- Use magnification and illumination to preserve orientation.
- Precurve a small hand file when the expected pathway changes direction.
- Stop when tactile feedback no longer matches the anatomical hypothesis.
During shaping
Let new information change the plan.
Working length, resistance, debris, irrigant movement, and file return all add information. If the established path stops reproducing, reassess coronal interference, blockage, curvature, and imaging before advancing.
The aim is not to make anatomy fit a preferred sequence. It is to preserve the original route while creating enough controlled access for disinfection and obturation. Refer or obtain further imaging when the pathway cannot be established without increasing procedural risk.
Professional education only. Apply current evidence, product instructions, clinical judgement, and the circumstances of the individual case.